Key Takeaways
- When a teenager refuses therapy, the refusal is almost always a signal about autonomy, not about how much they are struggling.
- The adolescent brain is undergoing a genuine developmental reorganisation — the emotional and reward systems mature earlier than the parts that regulate them. This is not stubbornness; it is neurobiology.
- Threats, ultimatums, and being “dragged” to a first appointment reliably backfire. Choice, honesty, and low-pressure entry points work far better.
- What happens in the first session matters more than most parents realise. Our adolescent work keeps the first appointment short, teen-led, and explicit about what the clinician will and won’t tell parents.
- The therapeutic alliance — the actual working relationship between the young person and the psychologist — is the strongest predictor of whether therapy helps. Modality matters; the relationship matters more.
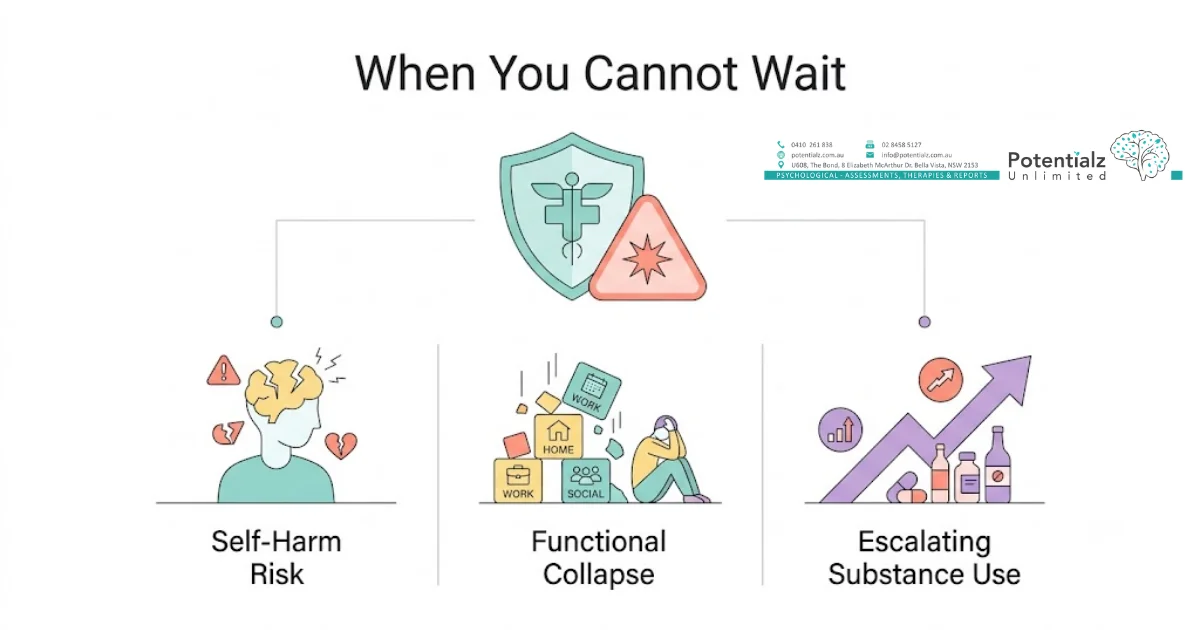
- There are situations where waiting is fine, and situations where it is not — self-harm, suicidal ideation, escalating substance use, and functional collapse at school are not “wait and see” territory.
- Cross-referral inside the practice: for children under 8 a play-based modality with our play therapist often fits better; for complex family systems, our senior Clinical Psychologist or other members of our Registered Psychologist team can see parents alongside the adolescent work.
- Asking for help is often the hardest part. The team knows that from clinical experience, and — for several team members — from their own experience of working through mental health as young adults.
”I’m Not Going. You Can’t Make Me.”
Most of the parents the practice speaks with about their teenager have already had some version of this conversation at home. It usually goes something like: “We think it might help to talk to someone.” Silence. Or: a flat “no.” Or: “You’re the one with the problem, not me.” Or the door closing.
If that is where you are — trying to get a genuinely struggling 13-, 15- or 17-year-old into a first appointment, and running into a wall — two things at the start.
First, the refusal is not a failure of your parenting, and it is not (usually) a sign that your teenager doesn’t care about their own life. It is much more often a signal about autonomy — about a young person who is doing the developmentally appropriate thing of pushing back against being organised by adults, at exactly the moment when what they need most looks a lot like being organised by an adult. That is a very hard bind, for them and for you.
Second, “no” at the beginning of this conversation is not the same as “no” at the end of it. A lot of the young people the practice now sees productively said no the first time, and sometimes the second and third time. The way we get from that first no to a workable first appointment matters — and there are things that reliably help, and things that reliably backfire.

This is a Potentialz Unlimited editorial piece drawing on our clinical team’s experience — an attempt to be honest with parents about both.
Why Adolescents Refuse Therapy — The Real Reasons
Before we talk about what to do, it is worth spending some time on what is actually happening when a teenager says no. In our clinical work with young people aged 12 to 17, the refusal almost always comes from one or a combination of the following places. Very rarely is it because they don’t think anything is wrong.
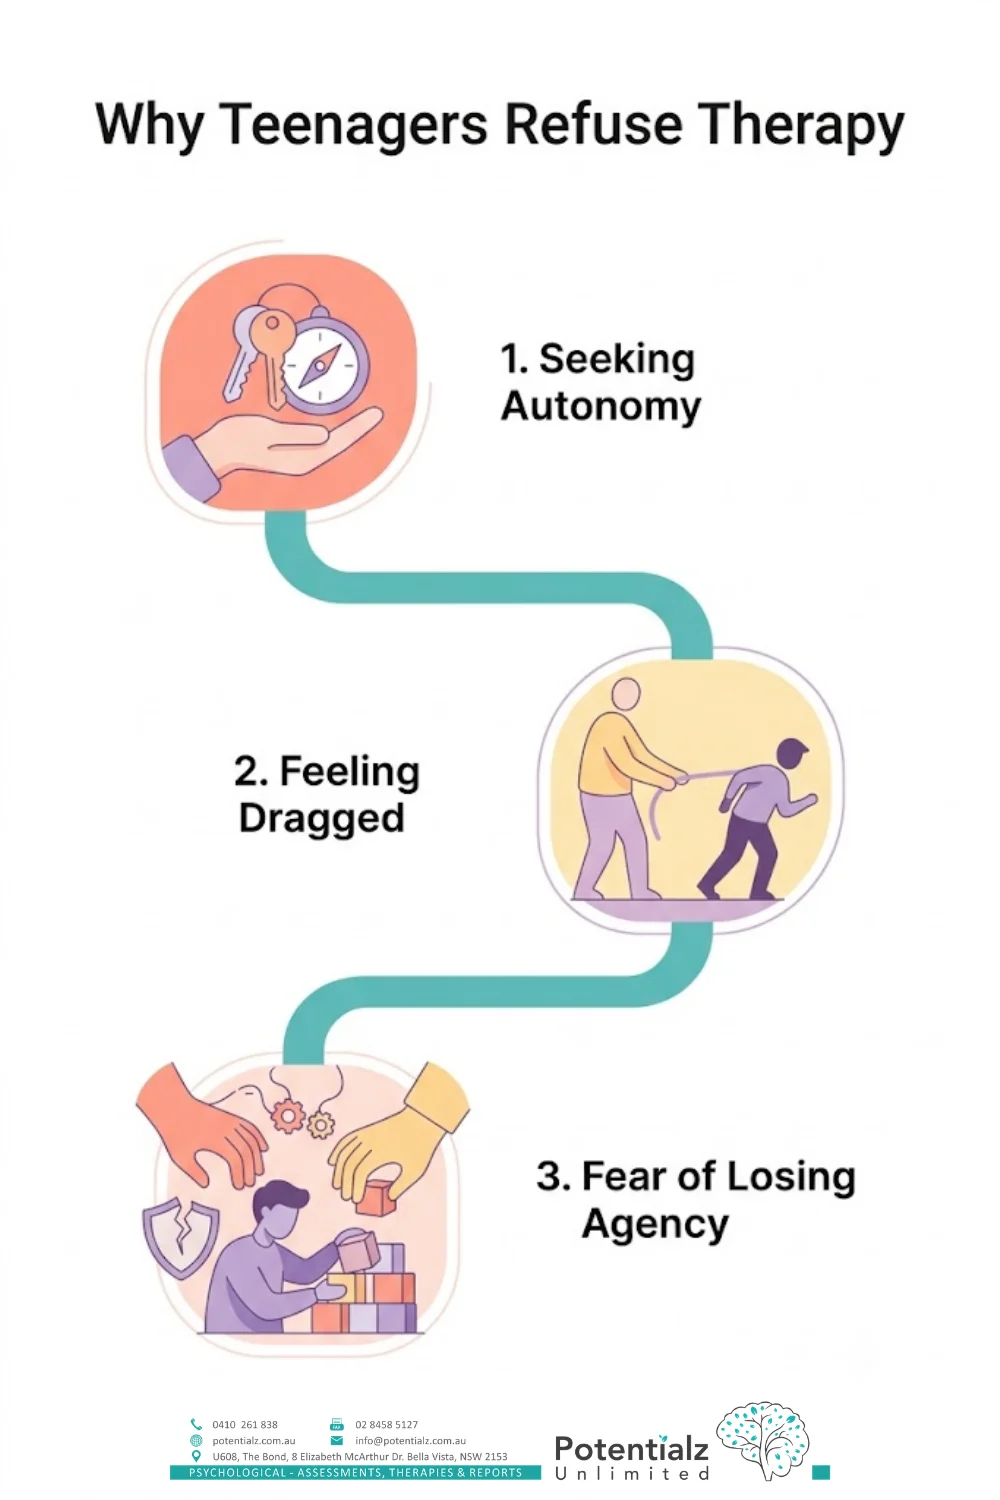
1. Autonomy — the developmental push to make your own choices. Adolescence is, at a basic developmental level, the process of becoming a separate person. That means testing where you end and your parents begin. Being told “you are going to therapy” — even kindly — hits that autonomy nerve directly. For many teenagers, saying yes to the appointment feels like saying yes to being managed. Saying no is a way of holding onto the sense that they get to decide something about their own life.
This is not a character defect. It is exactly what the developmental literature would predict.
2. The feeling of being dragged. There is a meaningful psychological difference between “I chose to come” and “I was made to come.” Adolescents are unusually attuned to the difference. A young person who arrives to a first appointment feeling dragged — through threats, guilt, or logistics they had no say in — arrives with their arms crossed, sometimes literally. That is a much harder starting point for the therapist, and, more importantly, it is a much harder starting point for the young person to genuinely benefit.
3. A previous bad experience. Many teenagers the practice meets have already seen someone — a school counsellor, a psychologist their parents chose after a difficult year, a GP who was warm but rushed. Not all of those experiences went well. Sometimes the young person felt talked down to. Sometimes they felt reported on. Sometimes they felt like the sessions were more about reassuring the adults than about them. If your teenager has said no to therapy, it is always worth asking, gently, whether something has already happened that they did not like.
4. Mistrust of adults in general. Adolescence involves a shift in whose opinions carry weight. Peers begin to matter more than parents in a lot of domains. Adults, as a category, can start to feel less trustworthy — not because your teenager has stopped loving you, but because the developmental job of this stage is to figure out how to operate in the world without you. Sitting down with an unfamiliar adult and telling them what is going on inside your head is, from that vantage point, a very big ask.
5. Stigma among peers. The generational picture has genuinely improved — teenagers today are more comfortable talking about mental health than any generation before them. But the picture is uneven. In a lot of friendship groups and school environments, seeing a psychologist is still something young people are careful about disclosing. The fear is not always that they will be judged for having a problem; sometimes it is a subtler fear of being redefined by their peers as “the one who is in therapy.”
6. Fear of losing agency. This is the one parents underestimate the most. When a teenager refuses therapy, part of what they are often protecting is the sense that their internal life is their own. They are worried that once they open up, everything they say will be relayed back to parents, teachers, or eventually a medical file. They are worried they will be diagnosed with something that follows them. They are worried that saying anything honest will trigger consequences they cannot control.
That fear is not paranoid. It is a reasonable question about how confidentiality works when you are a minor, and it deserves an honest answer.
The Adolescent Brain, in Plain English
There is a piece of neurobiology that helps a lot of parents make sense of what they are watching at home, so here is a short, plain-English version of it.
By adolescence, two systems in the brain are on quite different developmental timelines.
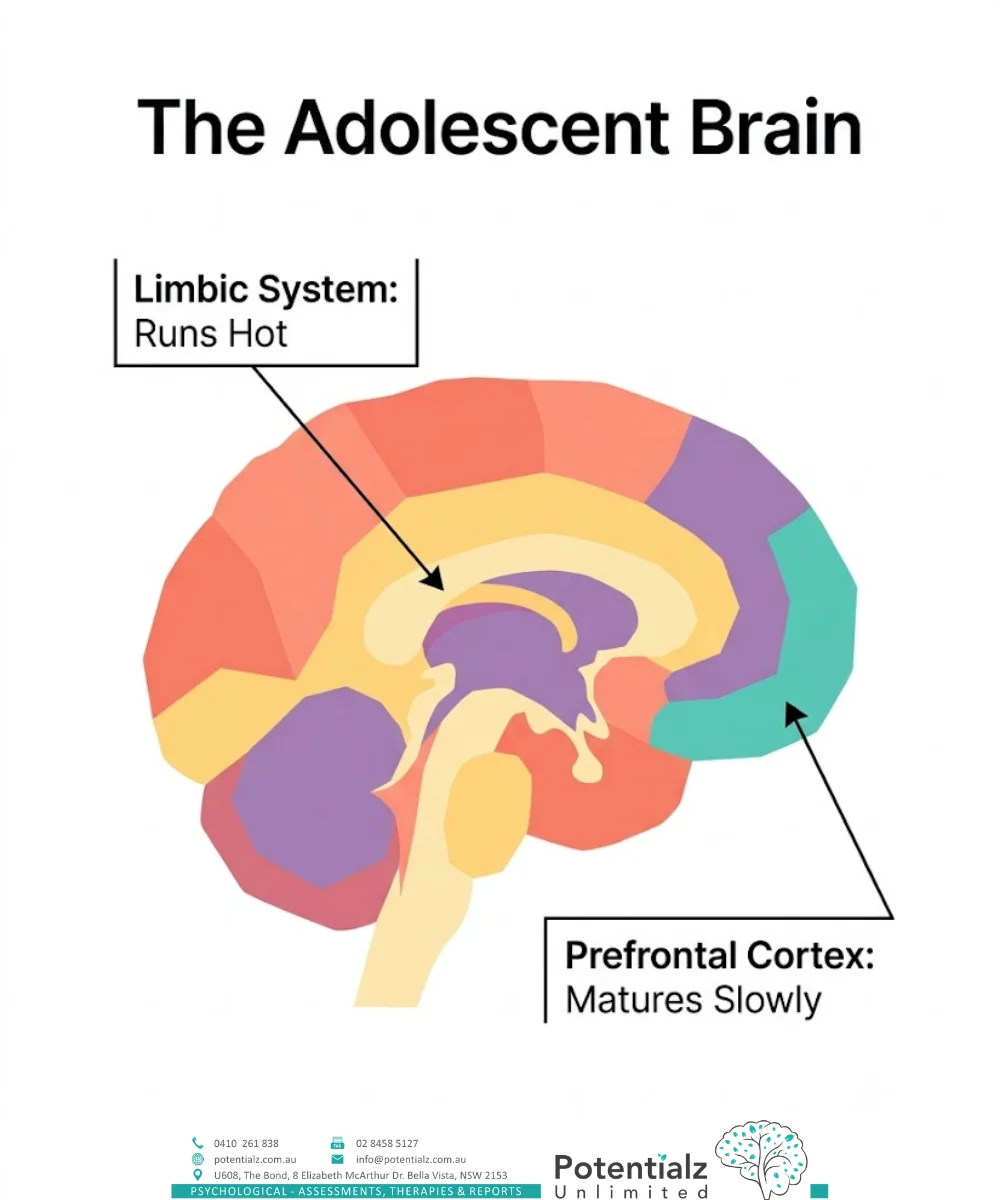
The first is the limbic system — the parts of the brain that generate emotion, reward-seeking, social motivation, and the strong pull of “I want this now.” In adolescence, this system is essentially running hot. The reward circuitry is more sensitive than it will ever be again. Emotional intensity is genuinely higher. Social feedback — especially from peers — lands harder than it does in either childhood or adulthood. This is a normal, temporary developmental state, and it exists for good evolutionary reasons: it is part of what motivates adolescents to explore, to bond outside the family, and to take the risks that eventually let them build an adult life.
The second is the prefrontal cortex — the part of the brain that plans, weighs consequences, and regulates impulses. This system matures much more slowly. It is not fully developed until the mid-twenties.
Adolescent decision-making, then, is not a broken version of adult decision-making. It is a system in which the accelerator has matured before the brakes. Laurence Steinberg, one of the most cited developmental scientists working on this, describes adolescence as a period of “heightened plasticity and vulnerability” — the brain is exquisitely sensitive to experience during these years, which is exactly why it is also exquisitely sensitive to the wrong kinds of experience. B. J. Casey and colleagues’ work on adolescent decision-making shows the same pattern in the neuroscience: adolescents are perfectly capable of good judgement in low-arousal, low-social situations, and much more likely than adults to be pulled off course in high-arousal or high-peer-influence ones.
For parents, three practical implications come out of this.
First, when your teenager says no to something that is clearly good for them, they are not being illogical — they are running the calculation through a brain that weights immediate emotional cost more heavily than delayed benefit. Refusing therapy right now feels better in the moment. The fact that it might help six weeks from now is a real thing to them, but it lands with less force.
Second, identity formation is one of the central tasks of adolescence. Everything that touches identity — including what problems you have, what help you accept, what labels you take on — is being handled by a system that is doing very serious work about who this person is becoming. Framing therapy as something that questions who they are will meet much more resistance than framing it as a tool they can use to become who they want to be.
Third, peer priority is not a rejection of the family. It is how a young person moves toward adulthood. This is one of the reasons that a psychologist who is not the parent, not the teacher, and not part of the young person’s peer group — a third-party adult with a clear role — can sometimes reach a teenager in a way that no one closer to them can.
What the Practice Does Differently With Adolescents
Because of everything above, the way the practice runs a first appointment with a 13- to 17-year-old is deliberately different from the way a first session with an adult might go. A few things the team holds to consistently.
Short first sessions. For many teenagers, an hour of talking to an unfamiliar adult about hard things is too much for a first meeting. The team is comfortable running a shorter, low-pressure first session where the goal is not to “get into the issues” but to figure out, together, whether this feels like a room and a person the young person could actually use. If the referral question is not discussed at all in that first session, that is fine. Something more important has been built — a decision the young person made about whether to come back.
The teen decides pacing. Once a working relationship exists, the young person has real say in what is worked on and how fast. That does not mean the clinician hands over the clinical direction — the psychologist is still the psychologist and brings what the evidence says about anxiety, depression, ADHD, trauma, and so on. But the pace, the order, and often the language belong to them. This is important for adolescents in particular, because the felt experience of being in charge of their own therapy is doing work — separately from the technique — every session.
No reporting back to parents beyond safety. This is the piece the clinician explains very clearly at the first session, with the young person and the parent in the room together. What is talked about is confidential. Parents will not routinely be told what has been said. The exceptions are the ones you would expect: risk of serious harm to self, risk of harm to others, and disclosures of abuse. If any of those come up, the clinician says so, and involves parents in a planned way — not as a surprise.
Young people are also told that if they want the clinician to share something with parents — a request, a boundary, a piece of information — the clinician is happy to do that with them, in the way they want. What the clinician will not do is act as an intelligence channel back to the adults.
Parents sometimes hear this and get worried. In practice, most parents end up feeling relieved by it, because it is exactly what makes the therapy actually work. A young person who trusts that what they say stays in the room is a young person who will say things.
Meeting them where they are. This is a phrase the team uses a lot, quite literally. Sessions do not start with the framing the clinician thinks a young person should have about their own life. Sessions start with the framing they arrive with — including the framing that they don’t really want to be here, that they’re not sure any of this helps, that their parents are overreacting, that the issue is school or friends or family and not them. All of that is real information. It is where the actual work begins, not something to be corrected before we can start.
What Parents Can Actually Do (and What to Avoid)
Given all of the above, here is what tends to work — and what tends to backfire — when you are trying to get a reluctant teenager to a first appointment.
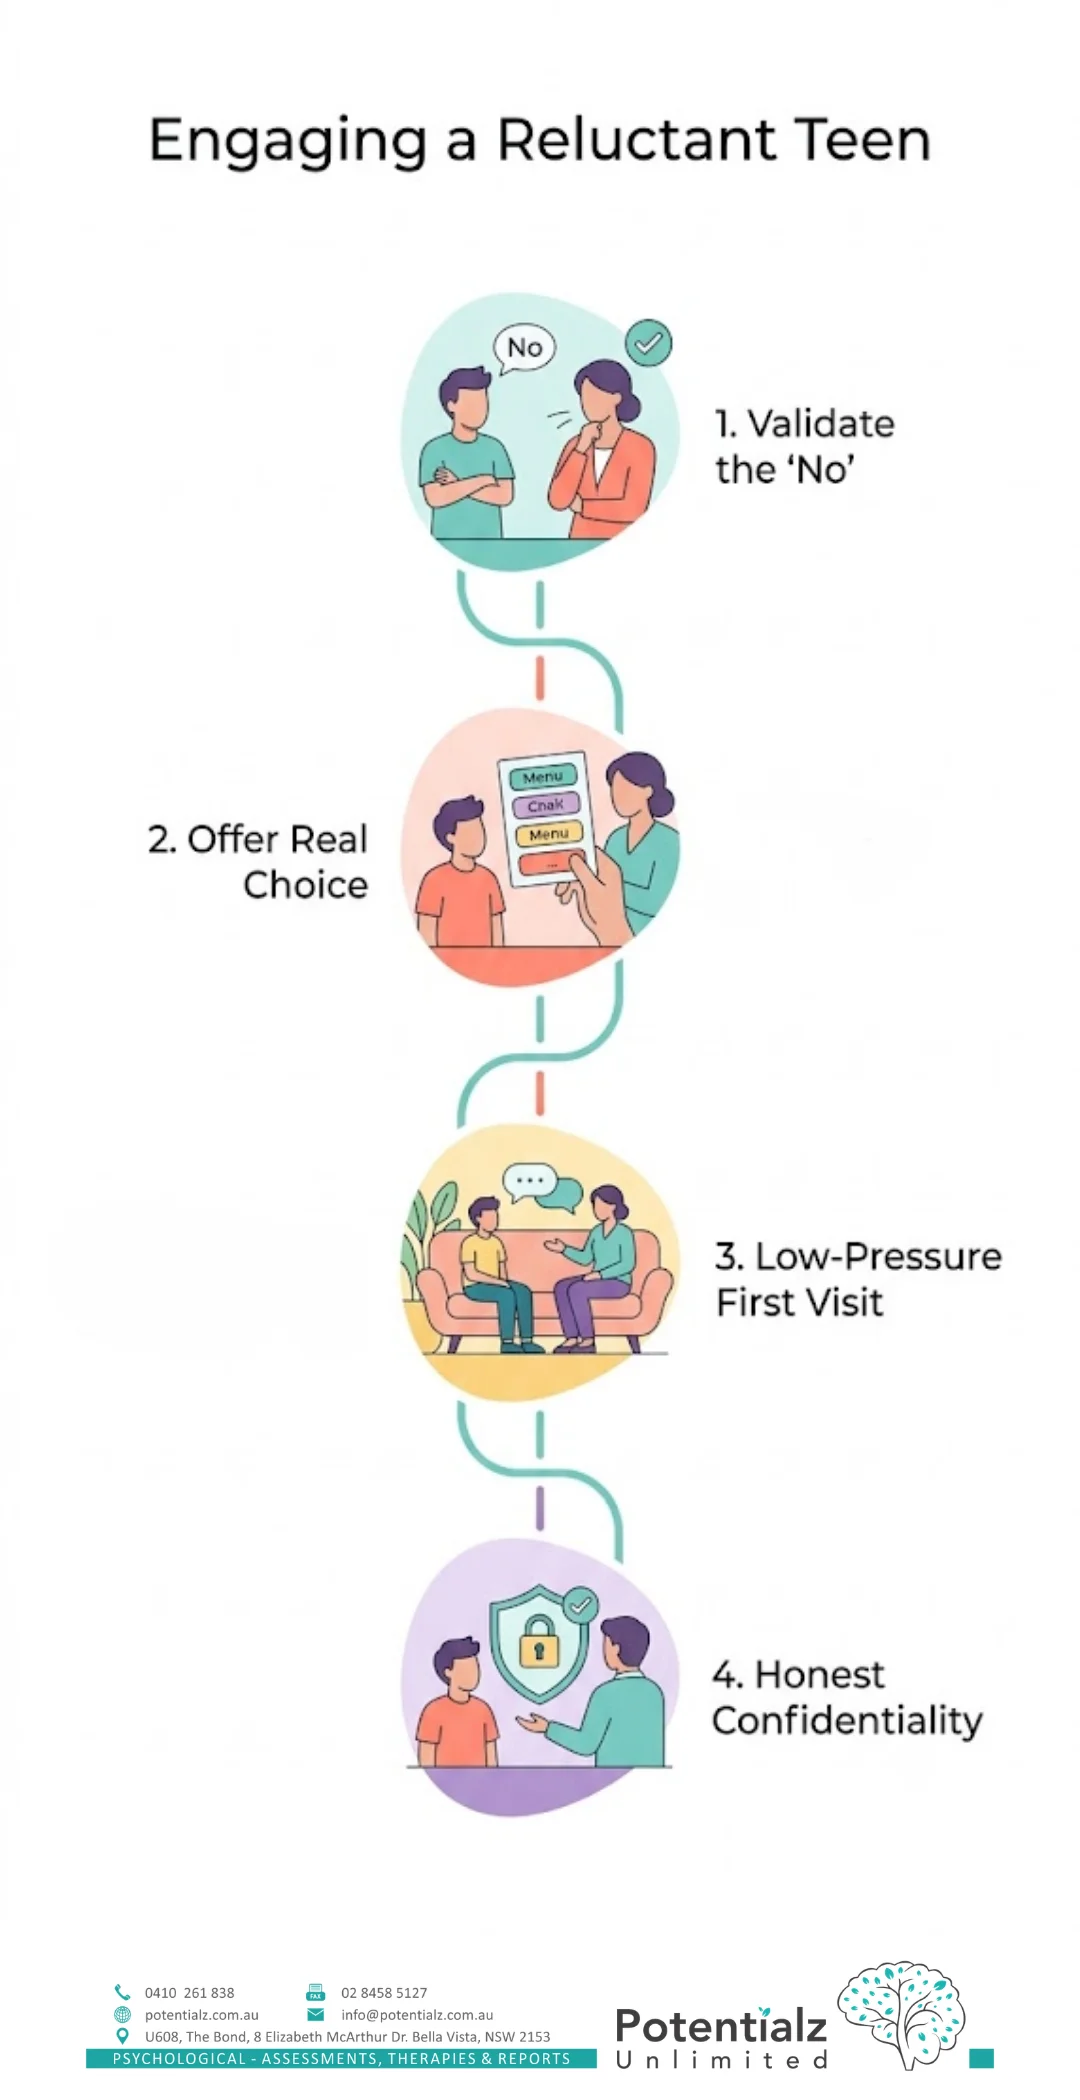
Validate the “no” before you push back on it. “I hear that you don’t want to. That makes sense — this feels like a big deal and you didn’t ask for it.” That single sentence, said and meant, changes the dynamic more than most parents expect. The reason is simple: when a young person feels that their objection has actually been heard, they don’t have to keep escalating it to be sure you understood.
Offer choice within a boundary. The boundary can be “I think it’s really important that you talk to someone.” The choice can be almost anything else. Which psychologist. Whether the first appointment is in person or telehealth. Whether you come to the waiting room or wait in the car. Whether they want a short phone chat with reception first. What time of day. Whether they want to bring a friend along for the drive over. Choice is the antidote to the “being dragged” feeling.
Do not threaten. Threats — taking away the phone, grounding, tying access to something they want to the appointment — reliably produce compliance and reliably produce a shut-down first session. If the goal is a body in a chair, threats work. If the goal is a young person who might actually benefit, threats set the therapy back.
Aim for a low-pressure first appointment. Sell it as a look-and-see, not a commitment. “Come to one appointment. If, after that appointment, you decide you don’t want to go back, we won’t force it.” Say this and mean it. Many teenagers who arrive on those terms come back for a second appointment, and eventually a third, entirely on their own steam — because the first one turned out to be less bad than they’d braced for.

Be honest about confidentiality. Before the first session, tell your teenager exactly what will and won’t be shared with you. If you don’t know, say you’ll ask reception, or wait and let the psychologist explain it in the room. Do not overpromise. Do not underpromise either. The one thing you should not do is imply that the therapist will act as an information source back to the family, because that primes exactly the kind of guardedness that makes therapy pointless.
Consider a brief phone chat with reception first. For a young person who is on the fence, a five-minute call with our reception — no appointment, no commitment, just a chance to hear what happens and ask questions — can be a much easier first step than booking. This is available; parents are welcome to ask for it.
Do not front-load the whole family. Sometimes parents want the first session to include everyone. That has its place, especially in family systems work. But for a hesitant adolescent, being outnumbered in the room at the first meeting can be a fast track to shutdown. Our team usually prefers to start with the young person alone (or with one parent briefly at the start), and bring others in later, in a considered way.
When It Is Fine to Wait — And When It Is Not
Not every reluctant teenager needs to be at a first appointment next week. There are situations where waiting a month, revisiting the conversation, and letting the young person come round on their own timeline is entirely appropriate. Adolescents do change their minds. Circumstances shift. Something at school breaks the log-jam.
But there are situations where waiting is not appropriate, and we want to be direct about them.
You should not wait if:
- Your teenager is self-harming, or you have found evidence of it, or a friend has raised it with you.
- Your teenager has talked about wanting to die, wanting to not be here, having thoughts about suicide, or having a plan.
- Substance use has escalated — new substances, more frequent use, using alone, using in the morning, using to cope.
- Their functioning at school has collapsed — not a bad term, but a genuine inability to attend, participate, or manage the workload, with no clear reason.
- There has been a sudden and significant change in personality, appetite, sleep, or social engagement — particularly withdrawal from things they used to care about.
- They have been through a specific event — a bereavement, an assault, an accident, a family crisis — and are not recovering.
In any of these situations, the calculus changes. It is still worth trying to bring the young person along willingly. But if that is not working, and the risk is real, seek help anyway — through your GP, through a crisis line, or directly through a psychology practice. In an acute crisis, call 000 or go to your nearest emergency department. The Kids Helpline (1800 55 1800) is free, confidential, and available 24/7, and is set up specifically for young people aged 5–25.
Consent is important. Safety is more important.
The Therapeutic Alliance Is the Actual Mechanism
If there is one piece of research to put into the hands of every parent worrying about which therapist to book, it is this: across decades of psychotherapy outcome research, the single most consistent predictor of whether therapy helps is the quality of the working relationship between the client and the therapist. Not the modality. Not the theoretical school. The alliance.
For adolescents in particular, that relationship — trust, feeling understood, sensing that the therapist is genuinely on their side and not just an extension of the adult system — is the load-bearing beam. If it is there, almost any evidence-based approach can be productive. If it isn’t there, no amount of technique compensates.
This has practical implications for parents. It means that “which therapist” is often a more important question than “which therapy”. It means that a young person who doesn’t click with the first psychologist they see is not doomed — they may just need a different room and a different person. It means that in the first few appointments, the goal is not primarily technique; it is the relationship. And it means that when your teenager says, after a couple of sessions, “I actually like her” — that is not soft data. That is the therapy starting to work.
Miller and Rollnick’s work on motivational interviewing — an evidence base originally developed for reluctant clients in substance use settings, and now used far more broadly — points in the same direction. When people feel pushed, they push back. When they feel heard, they move. A therapist working with a reluctant adolescent is not trying to talk them into anything. They are trying to build the kind of relationship in which the young person can hear their own reasons for change, in their own voice, and act on them.
What the Practice Offers at Potentialz Unlimited
At Potentialz Unlimited in Bella Vista, the Registered Psychologist team sees adolescents aged roughly 12 to 17, alongside children from age 8, young adults, and older adults. For teenagers, the modalities most commonly drawn on are Cognitive Behavioural Therapy (CBT), Acceptance and Commitment Therapy (ACT), and Solution-Focused Therapy — all evidence-based, all developmentally adaptable, and all designed to give young people practical tools they can actually use between sessions.
CBT is the usual starting point for anxiety and low mood — it gives the young person a clear model of how thoughts, feelings, and behaviour feed each other, and a set of tools for interrupting the loop. ACT is often the better fit for teenagers who are struggling with self-worth, identity, or big life questions — its emphasis on values, on being able to make room for difficult feelings without being run by them, tends to land well developmentally. Solution-Focused Therapy is a good option for young people who are tired of talking about the problem and want to build something forward.
For children under 8 whose parents contact the practice for adolescent-style therapy, the honest recommendation is often to see the practice’s play therapist instead — for younger children, a play-based modality frequently reaches emotional material more effectively than talk therapy, and the practice’s play therapy work is excellent.
For families where the adolescent’s difficulty is inseparable from a complex family system — a high-conflict separation, multi-generational dynamics, or a parent whose own history is very much in the picture — parent sessions alongside the adolescent work can be helpful, and other members of our clinical team at Potentialz see parents in exactly that role. This can be coordinated within the practice.
A short, honest note: several members of our Registered Psychologist team have worked through their own mental health as young adults, and one of the team has previously spoken publicly with school-aged young people about that journey. That does not put anyone inside your teenager’s experience — nothing does that — but it does mean the team has some real appreciation for how disproportionately hard the first step of asking for help can feel. That thread stays with the team in the room, and it is one of the reasons the first appointment is deliberately kept as low-key as possible.
What a First Six Weeks Often Looks Like
Parents frequently ask what the actual arc of therapy looks like for a teenager, especially when the young person has arrived reluctantly. The practice never promises a fixed course — every young person is different, and part of the work is figuring out the pacing that suits them — but a rough shape emerges often enough to be worth describing.
Session one is usually about the room, not the referral question. Most of the time is spent on who they are, what they like, what a normal week looks like, what they came here expecting, and what would make this a waste of their time. The clinician goes over confidentiality carefully. Somewhere near the end they might ask, gently, whether the young person has a sense of what their parents were worried about — but only if it feels like they have any interest in going there. If they don’t, that’s fine. The single most important thing that comes out of session one is a decision by the young person about whether to come back.
Sessions two and three tend to be where the referral question starts to come into focus, in the young person’s own language. Very often it turns out to be a somewhat different problem than the one the parents described — not because either the parent or the teenager is wrong, but because the young person’s inside view of what is going on is different from the outside view. That’s clinically useful information, not a problem.
Sessions four to six are usually where more explicit work begins — CBT skills, ACT exercises, Solution-Focused scaling — depending on what has emerged. By this point the young person often has a working sense of what therapy is for them, and can begin to shape the direction with more agency.
At around six sessions the clinician generally suggests a brief review — with the young person, and with parents if that fits — to talk about what has shifted, what hasn’t, and what the next stretch might focus on. Some young people are ready to wind down. Others want to keep going. Both are legitimate outcomes.
How Potentialz Can Help
If you are a parent trying to work out whether therapy is the right next step for your teenager, or you have decided it is and now you are trying to figure out how to get them in the door, you are welcome to contact the practice. If you or your teenager would prefer a short, no-obligation phone chat with reception before booking anything, that is available — just ask for it when you call.
Potentialz Unlimited’s Registered Psychologist team works with adolescents aged roughly 12 to 17, using CBT, ACT, and Solution-Focused Therapy, grounded in a strong therapeutic relationship. NDIS clients (self- and plan-managed) and private-pay bookings are both accepted.
Potentialz Unlimited Unit 608/8 Elizabeth Macarthur Drive, Bella Vista NSW 2153 Phone: 0410 261 838 Book: live.potentialz.com.au Hours: Monday–Friday 10am–7pm | Saturday and after-hours available | Telehealth via phone or Zoom
For children under 8, the practice will happily refer internally to the play therapist’s play-based work. For complex family systems where parent-only sessions are useful, this can be coordinated with other members of our clinical team.
Quiz: Test Your Understanding
1. When a teenager refuses therapy, what is most commonly driving the refusal? a) They do not think anything is wrong b) Autonomy, prior experience, and fear of losing agency ✓ c) A specific dislike of a particular psychologist d) Cost concerns
2. According to adolescent brain research, which of the following is true? a) The prefrontal cortex matures before the limbic system b) The limbic (emotional/reward) system matures earlier than the prefrontal (regulatory) system ✓ c) The adolescent brain is a smaller version of the adult brain d) Emotional intensity is lower in adolescence than in adulthood
3. What tends to be the most consistent predictor of therapy outcome, including for adolescents? a) The therapist’s specific modality (CBT vs ACT vs SFT) b) The therapeutic alliance — the quality of the working relationship ✓ c) The length of each session d) Whether parents attend every appointment
4. Which of the following would generally make sense to a reluctant teenager? a) Threatening to remove their phone if they do not attend b) Framing the first appointment as low-pressure and offering genuine choice within a firm boundary ✓ c) Booking a full family session as the first appointment without discussion d) Promising the therapist will keep parents informed of everything
5. Which of the following is NOT a “wait and see” situation? a) Mild irritability after a hard week at school b) Self-harm, suicidal ideation, escalating substance use, or functional collapse at school ✓ c) A short period of low motivation during exam block d) One argument with a friend
References
Casey, B. J., Jones, R. M., & Hare, T. A. (2008). The adolescent brain. Annals of the New York Academy of Sciences, 1124(1), 111–126. https://doi.org/10.1196/annals.1440.010
Casey, B. J., Getz, S., & Galvan, A. (2008). The adolescent brain. Developmental Review, 28(1), 62–77. https://doi.org/10.1016/j.dr.2007.08.003
Miller, W. R., & Rollnick, S. (2013). Motivational interviewing: Helping people change (3rd ed.). Guilford Press.
Norcross, J. C., & Lambert, M. J. (2018). Psychotherapy relationships that work III. Psychotherapy, 55(4), 303–315. https://doi.org/10.1037/pst0000193
Shirk, S. R., Karver, M. S., & Brown, R. (2011). The alliance in child and adolescent psychotherapy. Psychotherapy, 48(1), 17–24. https://doi.org/10.1037/a0022181
Steinberg, L. (2014). Age of opportunity: Lessons from the new science of adolescence. Houghton Mifflin Harcourt.
Steinberg, L. (2005). Cognitive and affective development in adolescence. Trends in Cognitive Sciences, 9(2), 69–74. https://doi.org/10.1016/j.tics.2004.12.005
Disclaimer
This article is a Potentialz Unlimited editorial piece drawing on our clinical team’s experience. It is for general education and information only, not clinical advice for your particular teenager. Potentialz Unlimited is a psychology practice based in Bella Vista NSW; our clinical team includes Registered and Clinical Psychologists (registered with AHPRA). Please consult a qualified health professional for your individual circumstances. If you or your child are experiencing a mental health crisis, contact your GP, call Lifeline on 13 11 14 or Kids Helpline on 1800 55 1800, or go to your nearest emergency department.
Crisis Resources
- Kids Helpline (ages 5–25, 24/7): 1800 55 1800
- Lifeline: 13 11 14 (24/7)
- Beyond Blue: 1300 22 4636
- 13YARN (Aboriginal and Torres Strait Islander crisis line): 13 92 76
- Emergency: 000
Related Reading
- Integrative Counselling for Teenagers: A Holistic Approach to Teen Mental Health
- Autism and Mental Health: Understanding Anxiety and Depression in Autistic Adults
- Impostor Syndrome: Why You Feel Like a Fraud — and How to Stop
- Sleepmaxxing vs CBT-I: The Evidence-Based Way to Actually Optimise Your Sleep
Need Professional Support?
If you're experiencing mental health concerns, our team is here to help.